


Two cases explore PSA and pathologic outcomes during an integrative protocol combining oral curcumin, artesunate, turkey tail mushroom, and dietary interventions in men with prostate adenocarcinoma.
Introduction
Prostate cancer is the second most commonly diagnosed cancer among men worldwide, with approximately 313,780 new cases and 35,770 deaths estimated in 2025. Despite advances in evaluation and treatment, incidence of distant-stage disease continues to increase across all age groups, the largest burden occurring among men age 70 and older, with median age of diagnosis between 67-69.[1]
Diagnosis typically involves prostate-specific antigen (PSA) testing, digital rectal examination (DRE), or a combination of both. In 2026, the American Urological Association (AUA) updated its guidelines regarding early detection of prostate cancer, recommending consideration of PSA screening beginning at age 45 in individuals at increased risk, including those with a family history of prostate cancer, Black race, or a history of germline mutations, with screening intervals determined by individual risk. [2] When initial screening suggests an abnormality, further evaluation may include imaging and prostate biopsy.
Although prostate cancer is frequently slow-growing, it remains an important cause of cancer-related morbidity and mortality, as only 37% of individuals reported routine screening tests with PSA. When detected early, it may be effectively managed through active surveillance or standard-of-care treatments depending on disease characteristics.
Treatment strategies are determined based on disease stage, overall health status, life expectancy and patient preference. These strategies include surgery, radiation, hormone therapy and chemotherapy. Radical prostatectomy may be utilized for localized or locally advanced disease. Radiotherapies including external beam and brachytherapy are the most common strategies to address prostate cancer, which can be used as monotherapy in low-risk cases. Side effects can include urinary disorders, erectile dysfunction, and radiation proctitis. Hormone therapy, or androgen deprivation therapy (ADT), aims to reduce or block the production of androgen signaling that fuel cancer growth, and is often used when cancer has spread beyond the prostate or in conjunction with radiation therapy. If necessary, chemotherapy or cryotherapy can also be employed. The choice among these treatments depends on various factors, including cancer stage, patient health, and potential side effects. [3]
Interest in complementary and integrative approaches to cancer care continues to increase. Recent studies suggest that more than 40% of patients with cancer report using complementary or alternative medicine during their cancer treatment. [4,5] Preclinical research has identified several botanical compounds with potential anticancer activity, although clinical evidence remains limited for many of these agents.
Curcumin:
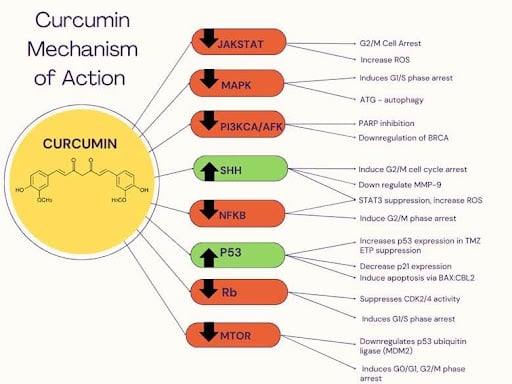
Curcumin is a polyphenolic compound derived from Curcuma longa. Preclinical and clinical studies identified multiple anti-cancer mechanisms in prostate cancer, including cell proliferation inhibition, inducing apoptosis, cell cycle arrest, inflammatory signaling modulation and production of reactive oxygen species (ROS). These mechanisms are largely achieved via inhibition of nuclear factor kappa B (NF-Kβ) and TNF-α. Murine models demonstrate activity on PI3K/Akt/mTOR axis pathway suppression to reduce proliferation. [6] Upregulation of p53 proteins via curcumin also impacts Bax and Bcl-2 to induce apoptosis in prostate cancer cell lines. Lastly, several studies show reduction of androgen receptor gene expression via NF-Kβ inhibition. This reduction reduces the downstream activity of cell proliferation and apoptosis inhibition of prostate cancer cells [7] Other genetic pathway impacts of curcumin have also been studied, including AP-1, MAPk, EGF, JAK2/STAT3 (Graphic 1). In Choi et al, 1440mg/day of curcumin showed PSA elevation suppression. Other human studies have shown curcumin alongside either chemotherapy or radiotherapy with some benefit noted in toleration of conventional treatments.[8] Of note, bioavailability of curcumin via oral supplementation poses challenges for therapeutic benefit, and while other forms of curcumin are available (such as intravenous), these remain experimental. Nonetheless, these findings provide a mechanistic rationale for further investigation of curcumin in prostate cancer; however, most evidence remains preclinical, and its clinical efficacy as an anticancer therapy has not been established.
Graphic 1.
Artesunate:
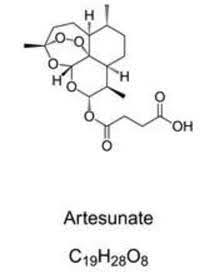
Artesunate, a semi-synthetic derivative of artemisinin from the Artemisia annua or wormwood plant, is a well-known anti-malarial medication widely available. It is currently studied for its anti-cancer benefit, including in prostate cancer. Its main mechanism of action, discovered in 2012, is through ferroptosis or iron dependent lipid peroxidation. Preclinical studies have demonstrated that artesunate may increase intracellular Fe²⁺ availability and reduce glutathione, thereby promoting lipid peroxidation. This process leads to excess ROSs and cell membrane damage resulting in cell death. Due to high iron requirements by tumor cells, this mechanism poses new opportunities for targeting tumor cells [9]. The success of ferroptosis depends on a variety of pathway factors both within the cancer cell and in its tumor microenvironment. Some of these components include COX/PGE2, Glutathione, P53 phosphorylation, Nrf2, PTEN/PI3K/mTOR [10]. It also exerts effects on androgen receptors via AR-DNMT3b pathway and suppresses growth of prostatic cancer cells [11]. Importantly, the evidence supporting artesunate as an anticancer therapy in prostate cancer remains primarily limited to cell-line and animal models. Because artesunate may affect iron metabolism, monitoring for iron deficiency and anemia may be appropriate when it is used clinically.
“Both patients demonstrated favorable PSA trajectories during follow-up, and one patient demonstrated a lower Gleason score and Grade on repeat biopsy.”
Case Series:
Given the overlapping mechanistic effects identified in preclinical studies of curcumin and artesunate and emerging evidence of them in solid cancer types, the combined use offers a compelling approach to prostate cancer treatment. Here we share two cases of males with a history of prostatic adenocarcinoma receiving a treatment protocol incorporating oral curcumin and artesunate, with additional use of turkey tail mushroom and dietary interventions. Neither patient received conventional anticancer therapy during the period described in this case series. Both patients consented to participate in AIMS (Advanced Integrative Medical Science) Institute’s AIMS Medical Outcomes Study (AMOS) (NCT04495790), a five-year prospective outcome studies of patient outcomes during and after receiving integrative care at the AIMS Institute.
Case 1:
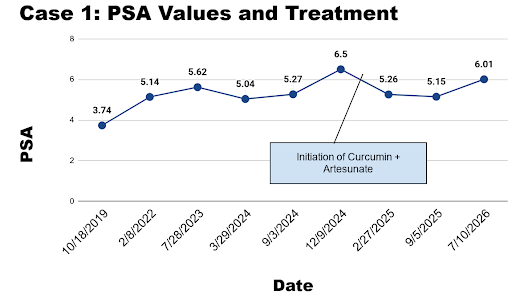
A 58-year-old male was diagnosed with prostate adenocarcinoma in December 2023 following a rising PSA level of 5.6 ng/mL in August 2023. Biopsy demonstrated adenocarcinoma in multiple cores with a Gleason score of 3+4=7, Grade 2, without a cribriform pattern or lymphovascular invasion (LVI), and was noted as aggressive. At the time of diagnosis, the patient was asymptomatic and had a normal complete blood count (CBC). He elected active surveillance, with potential future consideration of prostatectomy. At intake, the patient reported nightly alcohol consumption and a stressful work environment. On January 18, 2024, he initiated a protocol consisting of curcumin 1,000 mg twice daily Monday through Friday; artesunate 200 mg, two capsules twice daily on Saturday and Sunday; and turkey tail mushroom 1,500 mg twice daily. Dietary recommendations included intermittent fasting for at least 14 hours, and the patient independently initiated a ketogenic diet. Following initiation of this treatment protocol, PSA decreased to 5.26ng/mL and subsequently remained relatively stable below 6 ng/mL during follow-up (Graph 1). Repeat biopsy taken March 2025, revealed adenocarcinoma Gleason score 3+3, Grade 1 without LVI. He had not received any conventional therapies since diagnosis.
After approximately two years of treatment, the patient developed iron deficiency anemia in September 2025. Artesunate intake was reduced to once monthly. Subsequently, CBC and Ferritin levels improved with adjustments to this protocol and addition of meat to his diet. Signatera mutual residual disease testing on 6/1/2026 revealed negative findings.
Graph 1:
Case 2:
A 61-year-old male had a history of low-risk prostate cancer diagnosed in 2010, characterized as cT1c disease with a PSA of 2.6 ng/mL and Gleason score 3+3=6 in one biopsy core. In 2017–2018, he was found to have progression to intermediate-risk disease, characterized by cT1c disease, PSA of 12.8 ng/mL while receiving hormone therapy, and Gleason score 3+4=7.
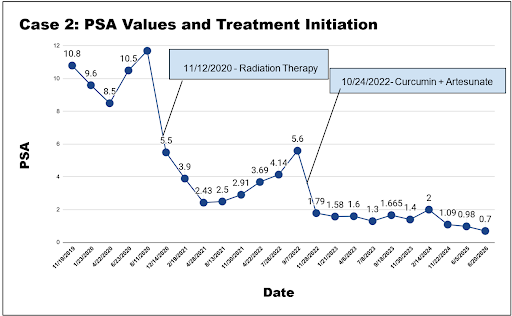
The patient initially pursued nutraceutical approaches. His PSA was 10.5 ng/mL on June 22, 2020. He subsequently underwent proton beam radiation therapy in November 2020. An increase in PSA was noted in 8/2022, and he was determined to have a biochemical recurrence with imaging showing abnormal signal at base of prostate equivocal for active prostate cancer recurrence. No biopsy was performed. In October 2022 (first intake), he was prescribed curcumin 1000mg twice per day Monday-Friday, and artesunate 200mg 2 capsules twice per day Saturday and Sunday, and turkey tail 1500mg twice daily. Following initiation of the protocol, PSA decreased from 5.6 ng/mL to below 2 ng/mL and subsequently remained stable, with a slight downward trend during follow-up (Graph 2). In April 2023, the patient developed low iron (48), Iron saturation (14%) without anemia. His treatment protocol adjusted to artesunate once weekly. Repeat iron studies in March 2026 demonstrated normalization of iron and iron saturation. The patient continues the protocol.
Discussion
These two cases provide preliminary clinical observations regarding the use of a non-conventional oral botanical protocol in patients with prostate adenocarcinoma undergoing PSA and pathologic surveillance. In both cases, PSA remained stable or decreased during the period of observation. In Case 1, repeat biopsy also demonstrated a lower Gleason score and Grade compared with the initial biopsy.
Preclinical studies investigating curcumin and artesunate as individual agents have demonstrated activity against prostate cancer cell lines and in animal models. Curcumin has been studied in relation to multiple signaling pathways involved in prostate cancer progression, including NF-κβ, TNF-α, PI3K/Akt/mTOR, and androgen receptor signaling. [6,7]
Artesunate has demonstrated anti-cancer activity through ferroptosis action by increasing Fe2+ and reducing GSH levels, thereby increasing lipid peroxidation of cancer cells. In prostate cancer models, artesunate also has shown androgen receptor expression suppression via the AR-DNMT3b pathway. [9-11] Adverse events of iron deficiency or iron deficiency anemia were noted in both cases and therefore employment of this protocol should consist of regular CBC and iron panel surveillance, and adjustment to the protocol if necessary.
While the findings of this case series support mechanistic activity of these two compounds shown in preclinical studies, the findings cannot establish that curcumin, artesunate or combinations are causative for the observed changes in outcome measures. Of note, other additional, non-standard of care interventions were employed alongside curcumin and artesunate, including Trametes versicolor mushroom, which is shown to potentiate NK cell induced cytotoxicity [12,13,14]. In addition, dietary measures including intermittent fasting, keto diets or vegetarian diets were also part of these patients’ treatment plans. This suggests additional potential benefits via management of blood sugar and metabolic health.
A greater intervention population, control measures, long term follow-up, and matched SEER data would ideally allow for more significant demonstration of this intervention over time. Additionally, use of imaging alongside PSA levels as well as MRD testing could further illuminate if these particular botanical interventions provides anti-cancer activity across all types of evaluation techniques.
Conclusion
This case series describes two patients with prostate adenocarcinoma who received an oral protocol incorporating curcumin and artesunate, along with turkey tail mushroom and dietary interventions, during clinical surveillance. Both patients demonstrated favorable PSA trajectories during follow-up, and one patient demonstrated a lower Gleason score and Grade on repeat biopsy.
These observations are consistent with preclinical evidence suggesting potential anticancer activity of curcumin and artesunate in prostate cancer; however, they do not establish clinical efficacy or causality. The development of iron deficiency or iron-deficiency anemia in both patients also highlights the importance of monitoring CBC and iron indices during artesunate use.
Prospective clinical studies are warranted to determine the safety, feasibility, and potential efficacy of curcumin and artesunate in prostate cancer and to clarify whether these agents may have a role as adjunctive interventions during active surveillance.



